


Abstract
We describe the case of a 70-year-old man with a long history of inguinal hernia who finally presented to the emergency department with a scrotal enterocutaneous fistula. This is a rare complication of an incarcerated/obstructed direct inguinal hernia. We performed exploratory laparotomy with resection of the perforated small bowel and end-to-end anastamosis of the ileal segment using the purse-string suture at the deep inguinal ring.
INTRODUCTION
Delayed presentation of inguinal hernia results in strangulation, incarceration, obstruction, and rarely fistula. In developing countries with limited resources, ignorance, financial constraints and lack of specialist medical knowledge, such complications associated with hernias are quite common and leads to increased morbidity and mortality. We report a case of scrotal enterocutaneous fistula, a rare complication of incarcerated inguinal hernia due to late presentation, neglect and lack of proper management.
CASE REPORT
We present a 70-year-old man with a left-sided inguinoscrotal swelling that he had ignored for almost 10 years. This inguino scrotal swelling was initially reducible, but for the month before presentation it had been irreducible. A week prior to presentation, the patient developed abdominal pain and constipation for which he used self-medication. He then noticed sloughing of the skin on the left scrotum and faeco-purulent discharge from the wound with symptomatic relief. After this development, the patient's family members brought him to the emergency department of our hospital.
On examination, his left groin had a visible inguino scrotal swelling with no tenderness and his left scrotum had a wound with faecal discharge. Blood investigations revealed anaemia (Hb 8 gm/dl) and elevated WBC count (16 000/mm3). Ultrasonography showed a bowel loop in the left inguinal region and scrotum. The diagnosis was of a scrotal enterocutaneous fistula secondary to spontaneous rupture of an obstructed inguinal hernia. I.V. fluid and broad spectrum antibiotics were administered and a transfusion of two units of blood given. Emergency exploratory laparotomy was performed. A 20 cm loop of incarcerated ileum with a 2 × 2 cm perforation about 60 cm from the ileocaecal junction was noted. There was no peritoneal contamination. The ileal loop was reduced, 10 cm of ileal segment was resected and end-to-end anastamosis performed. As the site of hernia, repair was found to be faecally contaminated, a mesh would have been at high risk of infection. Therefore, we preferred to close the deep inguinal ring with a purse-string suture only. The scrotal wound was debrided and daily dressing was done. After 48 h, the patient was started on oral feeds, which were well tolerated.
DISCUSSION
Scrotal enterocutaneous fistula is a rare complication with only 10 cases reported in the literature (five cases in children [1–4] and five in adults [5–9]). Of the adult cases, two were from Nigeria which revealed spontaneous rupture of Richter's hernia, two were from India and one from Pakistan. Scrotal enterocutaneous fistula is seen mainly in developing countries because of lack of medical knowledge, poverty, neglect, late presentation and lack of proper management.
Our patient developed this rare and avoidable complication of inguinal hernia because he initially ignored his problems and was neglected by his family (Fig. 1). The presence of the fistula allowed decompression of the bowel and temporary relief of the intestinal obstruction. Unrelieved strangulation will, however, increase the likelihood of septic complications and mortality associated with intestinal obstruction. Therefore, urgent surgical exploration with bowel resection and end-to-end anastomosis is necessary to avert this. We believe that appropriate and timely surgical intervention can prevent such drastic complications. With prolonged incarceration, there is a high risk of testicular ischaemia from vascular compression. This may progress to frank gangrene of the testis requiring orchidectomy.
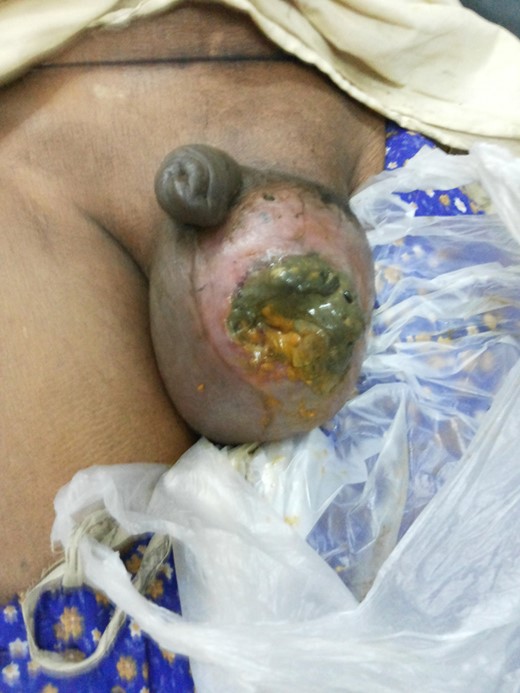
Scrotal enterocutaneous fistula: a rare initial presentation of inguinal hernia.
The principle of early referral and repair of inguinal hernia is key for prevention of this complication as well as associated morbidity and mortality. This case reflects the state of health care in developing countries, which needs to be addressed by concerned authorities.


