Journal Article

Hemoperitoneum secondary to intercostal arterial bleeding in a trauma patient

Journal of Surgical Case Reports, Volume 2017, Issue 1, January 2017, rjw194, https://doi.org/10.1093/jscr/rjw194
Published:
20 January 2017
Article history
Received:
14 September 2016
Accepted:
12 January 2017
Published:
20 January 2017

Abstract

Blunt trauma resulting in rib fractures can be associated with hemothorax, pneumothorax, pulmonary contusions or less frequently chest and abdominal wall hematomas. Our case describes the first report of hemoperitoneum secondary to intercostal arterial bleeding from blunt trauma in a patient on anticoagulation.

INTRODUCTION

Blunt trauma resulting in multiple rib fractures can be associated with intercostal bleeding [1]. There are multiple reports of intercostal arterial bleeding resulting in abdominal wall hematomas [2] and hemothorax [1] that require embolization [3] or even thoracotomy [4]. To our knowledge however, this is the first description in the literature demonstrating hemoperitoneum from intercostal arterial bleeding requiring laparotomy.

CASE REPORT
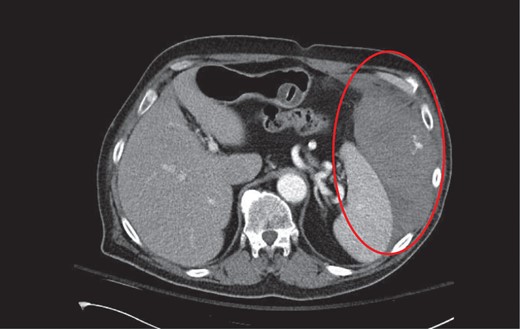
A 59-year-old male presented to our trauma center after sustaining a fall while transferring from a chair to wheelchair. He was on dabigatran for treatment of deep vein thrombosis in both lower extremities. His past medical history also included coronary artery disease, chronic kidney disease and a cerebral vascular accident. In the trauma bay, he reported left chest and left upper quadrant abdominal pain. On physical examination he was hemodynamically stable but tender to palpation over the left ninth and tenth ribs along the mid-axillary line. A Computed Tomography (CT) scan of the abdomen and pelvis with intravenous contrast demonstrated a large expanding left lateral chest wall hematoma, which appeared to be dissecting into the abdominal wall and peritoneum. Active contrast extravasation originating from an intercostal artery (Fig. 1) was associated with intraperitoneal blood in the perisplenic region and left paracolic gutter (Fig. 2). A selective angiogram of multiple left intercostal arteries and the deep circumflex iliac branch of the left external iliac artery did not show any active contrast extravasation. The patient was admitted to the intensive care unit for close monitoring and administered idarucizumab (praxbind) for reversal of his anticoagulation. Eight hours later, he developed worsening abdominal pain and became hemodynamically unstable with a systolic blood pressure of 80 mmHg. An exploratory laparotomy was then performed through a left subcostal incision. Upon entry into the peritoneal cavity 500 ml of clot was evacuated. A significant hematoma in the lateral abdominal wall just under the lower ribs had caused a tear in the peritoneum leading to the intraperitoneal blood. Active arterial bleeding could not be appreciated however a small amount of continuous bleeding from the left abdominal wall was controlled with suture plication. The patient received two units of packed red blood cells during the operation and was stable in the immediate postoperative setting. He was restarted on dabigatran on post-operative day four. His post-operative course was otherwise unremarkable and he was discharged home after five days.
CT axial with intravenous contrast demonstrating a large left abdominal wall hematoma with active contrast extravasation from an intercostal artery.
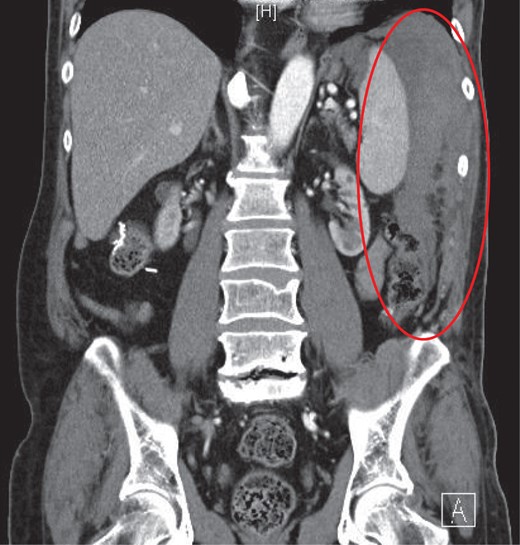
Figure 1:

CT axial with intravenous contrast demonstrating a large left abdominal wall hematoma with active contrast extravasation from an intercostal artery.

CT coronal with intravenous contrast demonstrating intraperitoneal blood products within the perisplenic region and left paracolic gutter.
Figure 2:

CT coronal with intravenous contrast demonstrating intraperitoneal blood products within the perisplenic region and left paracolic gutter.

DISCUSSION

Blunt thoracic trauma is often associated with rib fractures that may disrupt nearby structures including intercostal and internal mammary vasculature [1]. Such injuries can be associated with hemothorax, pneumothorax, pulmonary contusions and the development of an extrapleural hematoma that has a reported incidence of 7.1% [5].

In this report, the patient presented with hemoperitoneum from intercostal arterial bleeding. Clinically stable patients with normal hemodynamic parameters and radiographic features consistent with a non-expanding hematoma can be monitored in the intensive care unit with serial abdominal exams, laboratory studies, and reversal of coagulopathies [6]. In this situation, the patient was on dabigatran etexilate which is an oral prodrug converted by a serum esterase to dabigatran, a potent, direct, competitive inhibitor of thrombin [7]. Idarucizumab was used to reverse our patient's coagulopathy; it is an FDA-approved reversal agent for dabigatran and has shown to completely reverse the effects of dabigatran within minutes [8]. Idarucizumab is a monoclonal antibody fragment that binds dabigatran with an affinity that is 350 times greater than thrombin [8]. If unavailable, vitamin K, prothrombin complex concentrate, or fresh frozen plasma can be used in an attempt to reverse anticoagulation.

For patients presenting with rapidly expanding extrapleural hematomas, hemodynamic instability, or persistent bleeding from intercostal arterial branches, options for intervention include transcatheter arterial embolization (TAE) or surgical exploration [1, 4]. TAE has been reported as a safe and reliable technique in the management of blunt intercostal arterial injury associated with clinical deterioration [1]. In our patient, TAE was undertaken shortly after his arrival to our trauma center but did not reveal an active source of bleeding.

Surgical exploration should be considered with failure of angioembolization or when interventional radiology is not available. Strategies for operative exploration are dependent on the clinical scenario, hemodynamic stability, and the impact of associated injuries. In our case, a left-sided subcostal incision allowed access superiorly to the involved intercostal artery as well as inferiorly to evacuate the hematoma. Surgical plication of the suspected area was conducted and the tear in the periotneum was repaired during our fascial closure. At the end of the operation satisfactory hemostasis was achieved and we did not feel the need to place a drain.

In conclusion, hemoperitoneum secondary to intercostal arterial bleeding is an uncommon clinical finding. This can be managed with angioembolization if resources are available. Immediate reversal of medically-induced coagulopathy is also indicated. In patients with hemodynamic instability, expanding hematoma, or active contrast extravasation that cannot be embolized, surgical exploration should be entertained.

CONFLICT OF INTEREST STATEMENT

None declared.

REFERENCES

1

Chemelli
AP
,
Tahuerer
M
,
Wiedermann
F
,
Strasak
A
,
Klocker
J
,
Chemelli-Steingruber
IE
.
Transcatheter arterial embolization for the management of iatrogenic and blunt traumatic intercostal artery injuries
.
J Vasc Sur
2009
;
49
:
1505
–
13
.

2

Inoue
T
,
Iwamoto
T
,
Setsune
Y
.
Lateral abdominal wall hematoma due to blunt intercostal artery injury in a patient with serious comorbidities
.
J Em Med
2013
;
47
:
125
–
7
.

3

Nemoto
C
,
Ikegami
Y
,
Suzuki
T
,
Tsukada
Y
,
Abe
Y
,
Shimada
J
, et al. .
Repeated embolization of intercostal arteries after blunt chest injury
.
Gen Thorac Cardiovasc Surg
2013
;
62
:
696
–
9
.

4

Igai
H
,
Okumora
N
,
Ohata
K
,
Matsuoka
T
,
Kameyama
K
,
Nakagawa
T
.
Rapidly expanding extrapleural hematoma
.
Gen Thorac Cardiovasc Surg
2008
;
56
:
515
–
7
.

5

Chung
JH
,
Carr
RB
,
Stern
EJ
.
Extrapleural hematomas: imaging appearance, classification, and clinical significance
.
J of Thoracic Imaging
2011
;
26
:
218
–
23
.

6

Ishida
A
,
Hiraoka
A
,
Chikazawa
G
.
Spontaneous intercostal arterial rupture restrained by conservative management
.
Ann Vasc Dis
2014
;
7
:
430
–
32
.

7

Connolly
S
,
Ezekowitz
M
,
Yusuf
S
,
Eikelboom
J
,
Oldgren
J
,
Parekh
A
, et al. .
Dabigtran versus Warfarin in patients with Atrial Fibrillation
.
NEJM
2009
;
361
:
1139
–
51
.

8

Pollack
C
,
Reilly
P
,
Eikelboom
J
,
Glund
S
,
Verhamme
P
,
Bernstein
RA
, et al. .
Idarucizuman for Dabigatran Reversal
.
NEJM
2015
;
373
:
511
–
20
.

This is an Open Access article distributed under the terms of the Creative Commons Attribution Non-Commercial License (http://creativecommons.org/licenses/by-nc/4.0/), which permits non-commercial re-use, distribution, and reproduction in any medium, provided the original work is properly cited. For commercial re-use, please contact journals.permissions@oup.com
Close
This Feature Is Available To Subscribers Only

Sign In or Create an Account

Close

This PDF is available to Subscribers Only

View Article Abstract & Purchase Options

For full access to this pdf, sign in to an existing account, or purchase an annual subscription.

Close

Gift article access

As a benefit of your subscription, you can share temporary access to restricted articles.

Each link will stop working after 30 days or 10 uses. You may create up to 10 links in a 30 day period.

Please sign in to your personal account to gift article access.

Gift article access

Please create a link below to share with others. This will provide temporary access to this restricted article.

The link will stop working after 30 days or 10 uses. You may create up to 10 links in a 30 day period.

Gift articles remaining: --

Gift article access

The link will stop working after 30 days or 10 uses. You may create up to 10 links in a 30 day period.

Gift articles remaining: --

Gift article access

As a benefit of your subscription, you can share temporary access to restricted articles.

Each link will stop working after 30 days or 10 uses.

You have reached the limit of 10 links within a 30 day period