


Abstract
Sigmoid volvulus is a rare but life-threatening diagnosis in the paediatric population and has only been reported a handful of times in the literature. We describe the case of a 14-year-old boy with abdominal pain and diarrhoea who was diagnosed with a sigmoid volvulus after initially being managed for infectious gastroenteritis. The patient initially presented with a 5-day history of watery stool, 1-day history of profuse vomiting and colicky abdominal pain. Whilst admitted, the patient developed worsening abdominal pain, distention and hyperresonance to percussion. Computed tomography demonstrated a dilated sigmoid colon, with a mesenteric ‘whirl sign’ around the inferior mesenteric artery. The patient underwent a laparotomy, which confirmed a sigmoid volvulus, requiring an anterior resection. This case emphasises the importance for general surgeons to consider the rare diagnosis of sigmoid volvulus in children.
INTRODUCTION
Large bowel obstruction is a rare but life-threatening diagnosis in the paediatric population. Symptoms that would raise suspicion for sigmoid volvulus in the adults are often attributed to more benign conditions, such as gastroenteritis, in children. We describe the case of a 14-year-old boy with abdominal pain and diarrhoea who was diagnosed with a sigmoid volvulus after initially being managed for acute gastroenteritis.
CASE REPORT
The patient presented via ambulance to a regional emergency department with diarrhoea and abdominal pain. He had a 5-day history of watery diarrhoea, intermittent cramping abdominal pain and 24 h of profuse vomiting. He had no significant medical history, developmental delay or chronic constipation. In the emergency department, the patient required methoxyflurane and multiple doses of IV morphine. He was seen by a senior paediatrician and admitted with a provisional diagnosis of bacterial gastroenteritis. Soon after admission, he became tachycardic, hypertensive and pale with a distended and hyperresonant abdomen. There was no tenderness to palpation. Plain abdominal X-ray (AXR) showed dilated loops of the large bowel (coffee-bean sign) and faecal loading throughout the ascending and descending colon suspicious for a volvulus (Fig. 1). Computed tomography (CT) demonstrated a mesenteric ‘whirl sign’ around the inferior mesenteric artery and sigmoid mesentery (Fig. 2). An emergency laparotomy revealed a sigmoid volvulus with tight twist (Fig. 3). Although viable, the sigmoid and upper rectum were resected, and a side-to-side double-stapled primary anastomosis was created. Histopathology did not demonstrate aganglionosis.
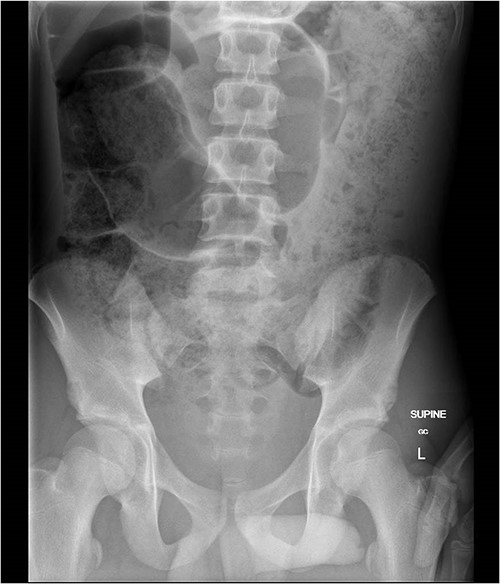
Abdominal plain X-ray demonstrated dilated loops of colon and ‘coffee-bean sign’.
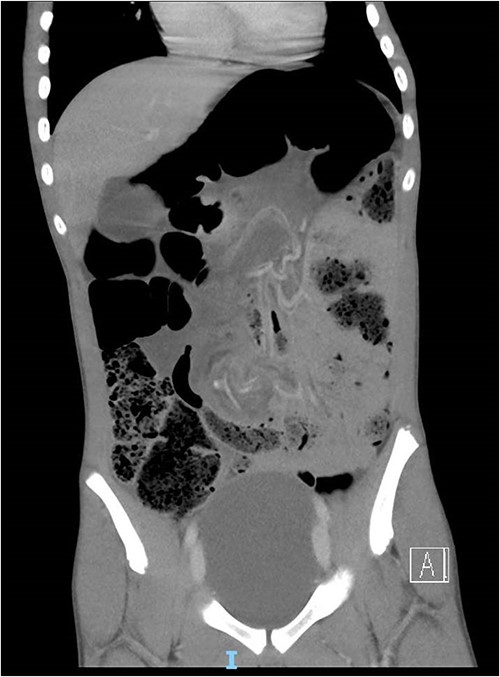
Computed tomography demonstrated a mesenteric ‘whirl sign’ around the inferior mesenteric artery and sigmoid mesentery. Dilated loops of sigmoid colon with proximal faecal loading.
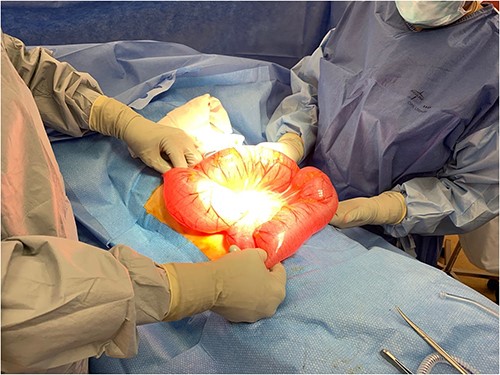
Intraoperative photograph demonstrating sigmoid volvulus.
DISCUSSION
In children presenting with vomiting and abdominal pain, sigmoid volvulus is often low of the list of diagnostic considerations due to the perception that it is a disease of the elderly. The incidence of sigmoid volvulus in the paediatric population is difficult to ascertain, with only case reports in the literature. Based on these reports, the median age of occurrence is 7 years old, with a male-to-female ratio of 3.5:1 [1]. Although the aetiology is not known in children, it may be associated with chronic constipation, Hirschsprung’s disease, imperforate anus and developmental delay [1].
There are often red flags that herald a more sinister pathology, such as the use of opiate pain relief. AXR is the first-line imaging modality in children with suspicion of an acute abdomen. CT can be performed after abnormal findings on an X-ray, such as the coffee-bean sign [2]. The use of AXR may only identify between 17 and 30% of sigmoid volvulus in children [3], so if the clinical suspicion remains high, a CT should still be obtained in the presence of a normal AXR.
Once the diagnosis is made, some authors proceed straight to exploratory laparotomy with bowel resection, whereas others recommend initial endoscopic detorsion if there are no signs of bowel compromise [4, 5]. Patients who have only had detorsion tend to have a high recurrence rate, up to 31% [6].
This case emphasises the importance of considering acute surgical conditions in children prior to diagnosing benign conditions. Although sigmoid volvulus is a rare condition, a missed diagnosis may lead to avoidable morbidity for patients.
CONFLICT OF INTEREST STATEMENT
None declared.
FUNDING
None.


